
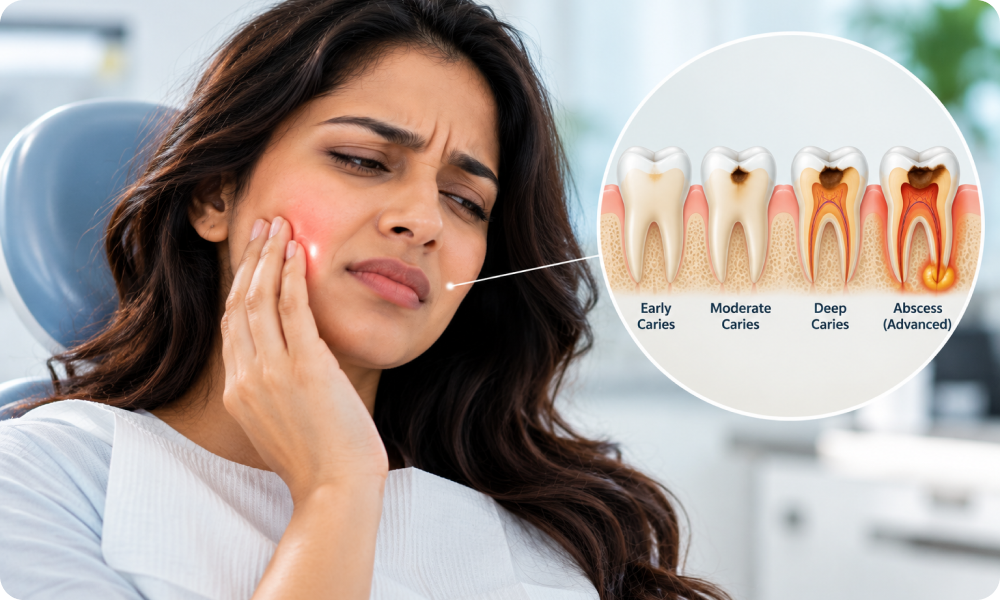
Dental decay is not a single event — it progresses through distinct stages,each requiring a different level of intervention.
Dental caries (tooth decay) is a dynamic, biofilm-mediated disease — the result of acid produced by oral bacteria breaking down fermentable carbohydrates. It is not caused by sugar alone; it is caused by the interaction of bacteria, diet, time, and host susceptibility. Understanding this means it can be interrupted at any stage.
Caries does not progress at a uniform rate. Early lesions can remain stable for years, while advanced lesions can escalate rapidly — especially in individuals with dry mouth, high sugar intake, or poor oral hygiene. The stage at which decay is detected determines both the complexity and cost of treatment.
At I Smile Clinic, we use ICDAS (International Caries Detection and Assessment System) criteria to classify lesions, combined with laser fluorescence detection for lesions not yet visible on X-ray. Early detection saves teeth — and significantly reduces treatment costs.
Book a consultation with our specialists and receive a personalized treatment plan.

No clinical evidence of caries. Preventive care maintains this status.

White spot lesion on the enamel surface — visible only when the tooth is dried. No cavitation yet. Fully reversible with fluoride and improved hygiene.

Decay has progressed through the enamel but not yet reached the dentine. Minimally invasive restoration or preventive resin can arrest the lesion.

Decay penetrates the dentine — causing sensitivity and requiring a filling. The cavity is now cavitated and self-arrest is unlikely without intervention.

Decay reaches the dental pulp, causing intense pain, abscess formation, and the need for root canal therapy to save the tooth.

Extensive destruction of the crown leaves insufficient tooth structure for a restoration. Extraction and replacement with an implant or bridge are required.

Clinical examination, bite-wing X-rays, and laser fluorescence scoring assign every tooth a caries risk stage.

Diet analysis, saliva testing, and medical history identify individual risk factors — determining how aggressively we need to intervene.

Stage 1–2 lesions receive remineralisation therapy. Stage 3 receives a filling. Stage 4 receives root canal therapy. Stage 5 is planned for extraction and replacement.

Fluoride varnish, fissure sealants, dietary counselling, and enhanced home care are tailored to your risk profile.

Higher-risk patients are recalled every 3–4 months until caries activity is controlled. All lesions are photographed for longitudinal comparison.
Yes — Stage 1 white spot lesions can be fully reversed with fluoride remineralisation and improved oral hygiene, without any drilling or filling. This is why early detection matters so much.
No. Early and moderate caries is often completely painless. Pain typically begins only when decay reaches the pulp — by which point the tooth requires root canal treatment, not just a filling. Regular check-ups catch decay before it hurts.
In adults with moderate risk, enamel caries typically takes 18–24 months to progress from a white spot to a cavity. In children or high-risk adults, this can happen much faster — in 6–12 months.
Yes. The back teeth (molars and premolars) have deep pits and fissures that trap bacteria and are difficult to clean. They account for the majority of cavities. Fissure sealants significantly reduce decay risk in these teeth.

Expert restorative treatments to repair damaged or decayed teeth and restore full dental function.

Complete preventive and restorative dental care for the whole family, ensuring optimal oral health at every age.

When decay or trauma infects the dental pulp, root canal treatment removes the source of pain and infection — preserving the natural tooth for years to come.
Our specialists will evaluate your case and design a treatment plan built around your goals.